China Ordered Rare Disease Clinics in Every Province by December and Left Payment Out

Every instruction raises the number of diagnosed patients. None addresses what they can be prescribed, or who pays.

Every instruction raises the number of diagnosed patients. None addresses what they can be prescribed, or who pays.

Coverage will call this a mental health guideline. One recommendation reaches into a commercial market and tells its providers to turn business away.

Coverage is calling these new AI rules. What they propose is replacing the single approval decision with supervised entry and permanent monitoring.
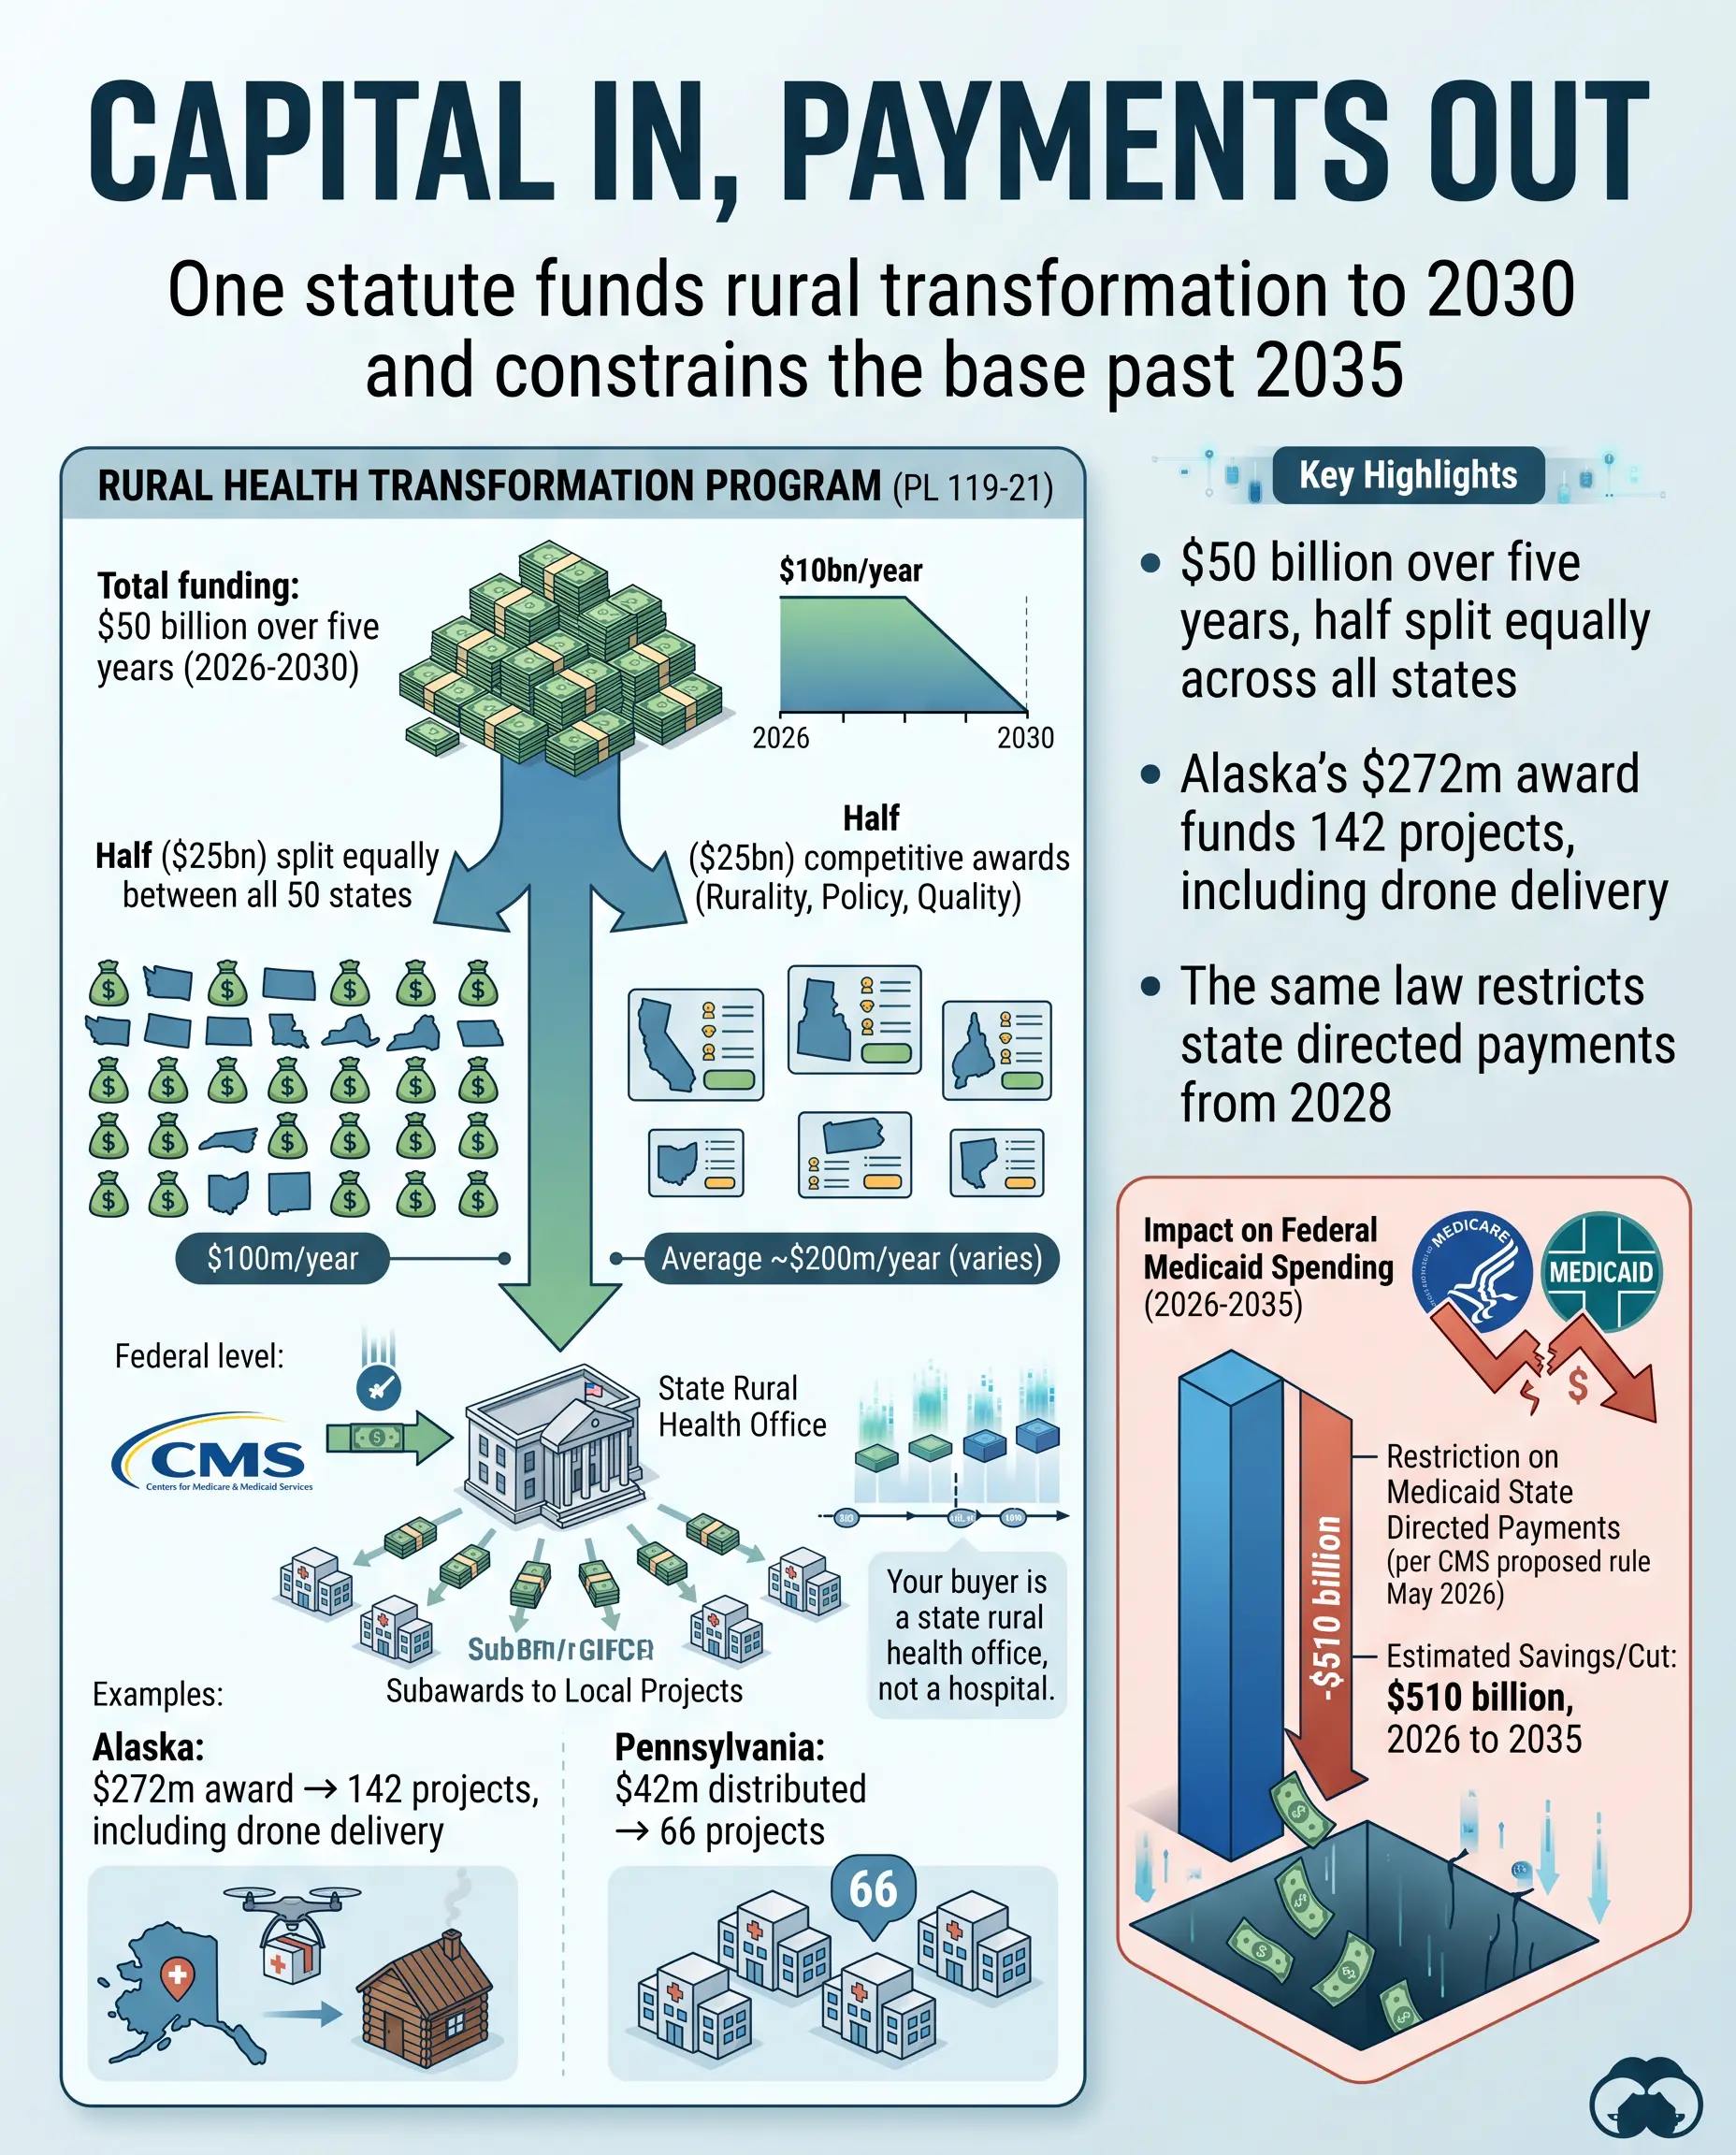
Half the pot is split equally, so award size is a weak proxy for market size. Your buyer is a state rural health office, not a hospital.

Three statutes across five years, discharged on one date. Evernorth says only the source of criteria changes, not the review process itself.

The approach came in 2017 as Philips prepared to close the plant. A site closure is a knowledge event before it is a cost event.

DOJ did not settle with a health plan. It settled with the in-home vendor that supplied the codes, and named the risk-share contract as the incentive.

Not a new theory of harm. It is the European Commission’s Copaxone decision run a second time, with two of the same corporate entities named.

Industry renegotiated what it pays FDA without changing what it gets. The clocks held. What expanded is the apparatus for verifying the money buys reviewers.

The piece of the federal prior authorization mandate that shipped five months early is the piece that cannot deny anything.